Breast Reconstruction is Individualized and Respects the Choices of the Patient
A mastectomy removes breast tissue to treat breast cancer. Reconstruction creates a breast shape, but it cannot restore the original breast exactly or guarantee a particular appearance, feeling or symmetry. A patient may choose reconstruction, use an external breast prosthesis or remain flat. The reconstructive consultation should support an informed choice rather than assume that every patient wants the same outcome.
Goals can include creating a breast mound, improving balance in clothing, preserving or reconstructing the nipple and areola when medically appropriate, or revising an earlier reconstruction. The safest and most suitable plan depends on both cancer care and reconstructive considerations.
Why Early Coordination Matters
A patient can ask for a plastic-surgery consultation soon after a mastectomy is being considered. Early discussion does not commit the patient to reconstruction. It allows the breast surgeon and plastic surgeon to consider whether mastectomy is required or whether a breast conserving approach can be utilized with re-arrangement of the remaining breast to fill the defect created by removing the cancer. In addition, the team considers whether the nipple can be preserved during the mastectomy or if it requires removal, where incisions should be placed to provide access to the cancer and optimal cosmesis, and whether the reconstruction may occur immediately following the cancer surgery if it must be delayed until after treatment.
If the mastectomy has already been performed, delayed reconstruction may still be possible months or years later. Prior radiation, scars, tissue quality and health may change the available techniques but do not automatically rule out reconstruction.
Immediate reconstruction begins during the same operation as the mastectomy. Delayed reconstruction is not performed at the same time as the mastectomy; the reconstruction begins at a later time. A staged reconstruction is a reconstruction that requires more than one operation to complete and may begin either immediately following mastectomy (immediate reconstruction) or at a later time (delayed reconstruction). Immediate reconstruction may allow preservation of more of the breast skin and can reduce the number of separate operations for some patients. However, the final reconstruction may still require additional stages, and immediate reconstruction is not appropriate for every treatment plan. Here is an example of the progress of immediate reconstruction at the time of mastectomy: 1. Cancer surgery (the mastectomy my be skin-sparing or nipple sparing depending on the oncologic operation), place a tissue expander in the area where the breast was removed, closure of the skin. The breast expander will be gradually expanded, either every week or every other week, with saline during office visits, until the desired expansion is achieved. 2. During a second stage, the tissue expander is removed and replaced with a permanent implant. Also during this stage, reshaping of the breast mound and fat grafting may be performed to add soft tissue coverage give the breast a more natural contour and also to help pad any areas of discomfort.
Delayed reconstruction is not performed at the same time as the mastectomy. It is typically performed after completion of all adjuvant therapy including chemotherapy, and radiation, or simply after the patient has recovered and is ready for reconstruction. A delayed reconstruction may still utilize a staged plan. The first stage, which begins following adjuvant therapy may begin with placement of a temporary tissue expander to stretch the skin and subcutaneous tissue so that it can create the shape of a natural breast and so that it can accommodate a breast implant. The second stage is removal of the tissue expander, reshaping the breast and placement of the permanent implant. Fat grafting and nipple reconstruction as well as re-shaping of the breast may occur during a third operation. Timing is determined with the cancer and reconstructive teams.
Implant-Based Reconstruction
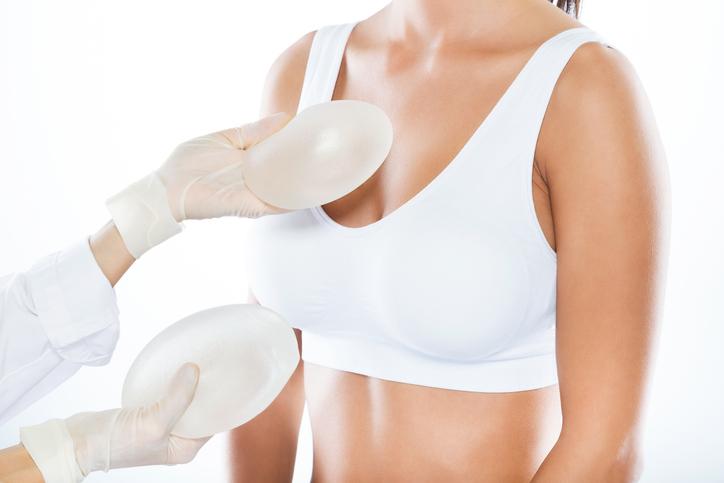
Implant-based reconstruction uses a saline- or silicone-filled breast implant to create the breast mound. Some patients may be candidates for direct-to-implant reconstruction. Others first receive a tissue expander that is gradually filled and later exchanged for a permanent implant.
The plan may involve use of acellular dermal matrix or surgical mesh to cover the implant and support the reconstruction, fat grafting or later contour adjustments. Implants are not lifetime devices. Future imaging, monitoring, replacement or removal may be needed, and implant-related concerns can include infection, exposure, rupture, malposition, rippling, implant loss/removal, and capsular contracture. Also, there are uncommon implant malignancies, associated with implants, particularly textured implants including breast implant associated ALCL. The FDA recommends ultrasound or MRI after 5 years after silicone implant placement and every 2-3 years thereafter. Saline implants do not have the same screening requirements.
Tissue-Based or Flap Reconstruction
Tissue-based reconstruction uses skin, fat and sometimes muscle, from another part of the body, to create the breast mound. Depending on the technique, muscle may be spared, as with the DIEP/PAP flaps, or may be included as part of the reconstruction as with TRAM or latissimus based flaps. Tissue based reconstruction may eliminate the need for an implant, although combined flap and implant approaches are sometimes used. Depending on the operation, tissue may remain attached to its blood supply or be transferred and reconnected using microsurgery. Potential donor areas include the abdomen, back, thigh or buttock. Not every technique is appropriate for every patient or offered by every surgical team.
Flap reconstruction can create the breast mound using the patient’s own tissue. In some instances, flap reconstructions can avoid the need for an implant, and in other instances, they are combined with an implant, especially when the transferred tissue alone contains little fat volume and will not likely provide the desired volume. The flap typically behaves more like the patient’s own soft tissue and can change with weight fluctuations and aging, but it creates a second surgical site and generally requires a more extensive operation and recovery. Donor-site strength, scarring, contour and healing must be considered along with the breast result. No flap method is universally best.
Radiation and Other Cancer Treatment
Radiation can affect tissue vascularity, skin quality, elasticity, skin flexibility, wound healing, fibrosis, and the appearance of reconstructed tissue. Radiation can affect implant reconstruction resulting in capsular fibrosis and capsular contracture, pain, tissue thinning, wound dehiscence and implant exposure, difficulty with expansion and implant failure and need for removal. The likelihood of a successful implant based reconstruction following radiation is around 50 percent. Radiation can also affect a flap reconstruction resulting in fibrosis, volume and shape changes or contour deformities and skin thinning. For this reason, flaps are typically delayed until 6 months after radiation is completed. Radiation does not lead to the same recommendation for every patient. The expected radiation field and timing should be discussed before surgery whenever possible.
Systemic chemotherapy, targeted therapy and other treatments may also affect operative timing depending on the blood counts, oncologic plan and healing. The oncology team determines cancer treatment; the reconstructive plan should be coordinated around and should not compromise or unnecessarily delay indicated cancer treatment.
Nipple-Sparing and Skin-Sparing Mastectomy
A skin sparing mastectomy preserves most of the breast skin envelope but removes the nipple areolar complex. By contrast, the nipple sparing mastectomy preserves both the breast skin envelope and the nipple areolar complex when oncologically and anatomically possible. Eligibility depends on the cancer location and extent, breast anatomy, tissue perfusion and patient risk factors. Preserving the nipple does not guarantee normal sensation or survival of all preserved tissue. Mastectomy itself disrupts sensory nerves, so substantial numbness is common, although newer nipple sensory preserving operations have been developed.
When the nipple and areola cannot be preserved, reconstruction or medical tattooing may be considered at a later stage. Some patients choose not to recreate the nipple and areola.
Symmetry, Fat Grafting and Revision
Reconstruction is frequently a process rather than one finished operation. Later procedures may adjust scars, contour, implant position or the transition between the breast and chest. Fat grafting may be used in selected areas, and a lift, reduction or augmentation of the opposite breast may be considered to improve balance.
Perfect symmetry cannot be guaranteed. The reconstructed breast and natural breast can age, change weight and respond to treatment differently. The number and timing of stages should be discussed before the first operation whenever possible.
Who May Be Evaluated?
Evaluation may be appropriate for a patient who is planning a mastectomy, has already completed mastectomy, is dissatisfied with an earlier reconstruction or has an implant- or flap-related concern. Health conditions, nicotine use, nutrition, body weight, previous abdominal or chest surgery and the ability to complete follow-up can affect candidacy and timing.
Some patients need medical optimization before reconstruction. Others may be better served by a different method, a delayed operation or an aesthetic flat closure A website cannot determine candidacy without examination and review of the cancer-treatment history.
Recovery and Follow-Up
Recovery varies widely. Implant exchange is different from a first-stage expander operation, and both differ from flap reconstruction. A hospital stay, surgical drains, support garments and help at home may be required depending on the procedure. Walking usually begins early, while lifting, upper-body strain and strenuous exercise remain restricted until the surgical team provides clearance.
Long-term follow-up remains important. Patients should continue breast-cancer surveillance as directed and should report new breast, chest-wall, implant, scar or donor-site concerns. Following mastectomy, routine screening mammography of the reconstructed breast is typically not performed; surveillance is primarily clinical with imaging when there is a new finding or symptom. If the opposite breast is preserved, than it continues appropriate screening. Imaging recommendations can also vary after nipple sparing mastectomy and some autologous reconstructions. Separately, silicone implants have FDA-recommended imaging to assess implant integrity.
Risks and Realistic Expectations
Potential risks include bleeding, infection, fluid collection, delayed wound healing, skin or nipple loss, breast or donor-site sensation changes, asymmetry, fat necrosis, unfavorable scarring, blood clots, anesthesia complications and the need for additional surgery. Implant reconstruction has implant-specific risks. Flap reconstruction has donor-site weakness, bulge, hernia wound dehiscence or seroma, and blood-supply risks, including partial or complete flap loss.
Reconstruction may help restore breast shape and balance, but it cannot recreate the original breast exactly, restore normal sensation reliably, or guarantee a particular cosmetic or emotional outcome. Goals, tradeoffs and acceptable staging should be discussed openly during consultation.